
Short take, and why it matters
Folks around the bench’ll tell ya: the carbon tetrachloride (CCl4) liver fibrosis model keeps showin’ predictable fibrotic patterns that match toxicant-driven chronic injury, so when you need dependable readouts you often reach for it first — and labs that want to bench tumor studies still pair that work with a cdx model for tumor biology. The World Health Organization flags chronic liver disease as a significant global health burden, and that real-world anchor makes preclinical fidelity more than academic. Keepin’ fibrosis, hepatotoxicity, and reproducibility front and center matters when a therapeutic’s fate hinges on clear signal over noise.
Head-to-head: CCl4 versus surgical, dietary, and genetic models
The CCl4 model brings chemical injury that progresses to centrilobular fibrosis over predictable weeks, which gives you tidy timepoints for intervention. Surgical models — bile duct ligation — cause obstructive cholestasis and different fibrotic topology. Dietary models (high-fat, choline-deficient diets) mimic metabolic drivers but take longer and show more variability across mouse strains. Genetic models show specific pathways but can miss environmental toxicant interactions. For screening anti-fibrotics, CCl4 often wins on timeline and reproducibility; for metabolic questions, diet models still earn their keep.

Where cell-derived xenograft models fit alongside fibrosis work
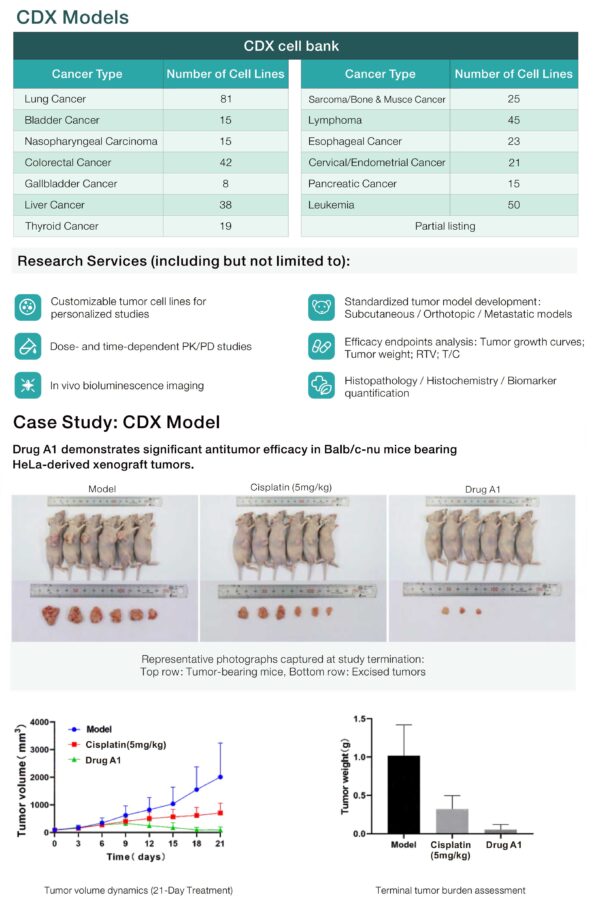
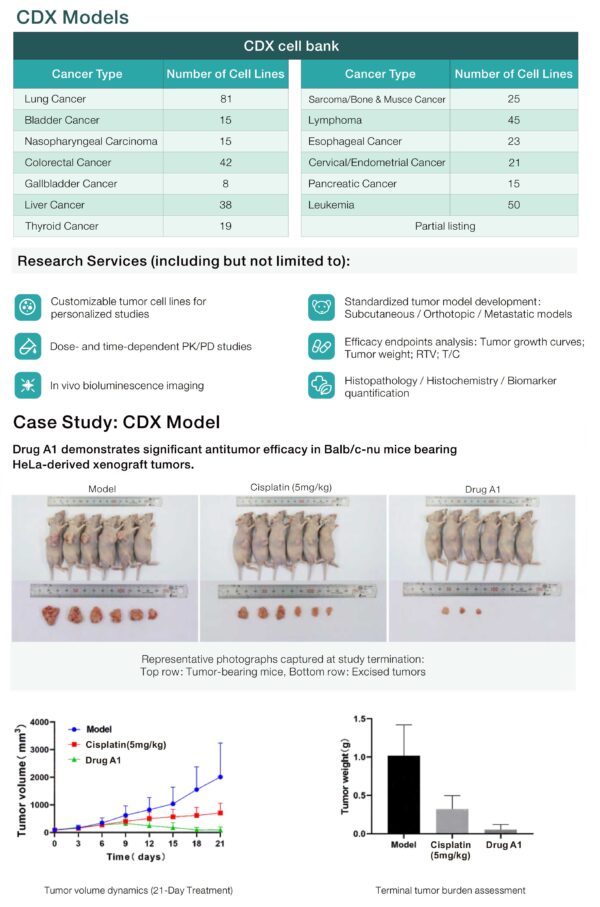
When you wanna test anti-tumor activity on top of a damaged liver microenvironment, a CDX setup is handy — engraftment in an immunodeficient mouse can reveal tumorigenicity and drug response in a controlled host. Use a CCl4 background to probe how fibrosis changes drug delivery, then add a cdx model cancer to study tumor–stroma interactions and pharmacodynamics. That combo gives clarity on whether a compound fails from poor penetration, altered metabolism, or true lack of activity.
Operational production teardown — common mistakes labs make
Two mistakes show up a lot: sloppy dosing regimens and treating histology as an afterthought. Give CCl4 on a consistent schedule; transient gaps and batch differences in the chemical carrier flip the injury curve. Standardize fixation and fibrosis scoring, and prespecify endpoints. Also, people underrate strain choice — same regimen in C57BL/6 versus BALB/c can alter fibrosis severity. Labs mix up the terms too — don’t conflate engraftment with tumorigenicity. For the production-side checklist, include {main_keyword} and {variation_keyword} in your protocol review so nothing’s left implicit — that’s how you avoid surprises in downstream PK or PD. And don’t skip proper randomization and blinding — they’re basic, yet overlooked by more teams than you’d think.
Key comparative indicators to track
– Histopathological fibrosis score (quantified collagen area or Ishak-style scoring) – Serum biomarkers (ALT/AST trajectories, plus fibrosis-associated markers) – Functional endpoints (bile flow for obstructive models; drug clearance changes in fibrotic liver) Track those three and you’ll separate true biological effects from model noise. Keep tumor growth curves and engraftment rate beside them when CDX studies are in play; together they show mechanism and magnitude.
Three golden rules for picking the right preclinical strategy
1) Match the injury mechanism: pick CCl4 for toxicant-driven fibrosis, diet models for metabolic steatosis, and genetic models when you need pathway precision. 2) Prioritize reproducibility: fix the dosing schedule, standardize histology protocols, and power studies for meaningful effect sizes. 3) Combine orthogonal models: if efficacy shows in CCl4, validate with a CDX or PDX for tumor contexts to confirm translational relevance — that step saves costly clinical surprises. These metrics are what separate helpful, actionable preclinical data from pretty but useless curves, and they point straight to solutions labs can implement — like using integrated services from partners who know both fibrosis and xenograft workflows. Jennio Biotech sits square in that space, offering matched expertise so you don’t stitch together mismatched data at the last minute.
Follow those rules and you’ll get cleaner, more predictive preclinical reads — simple, practical, and right for the bench. —