
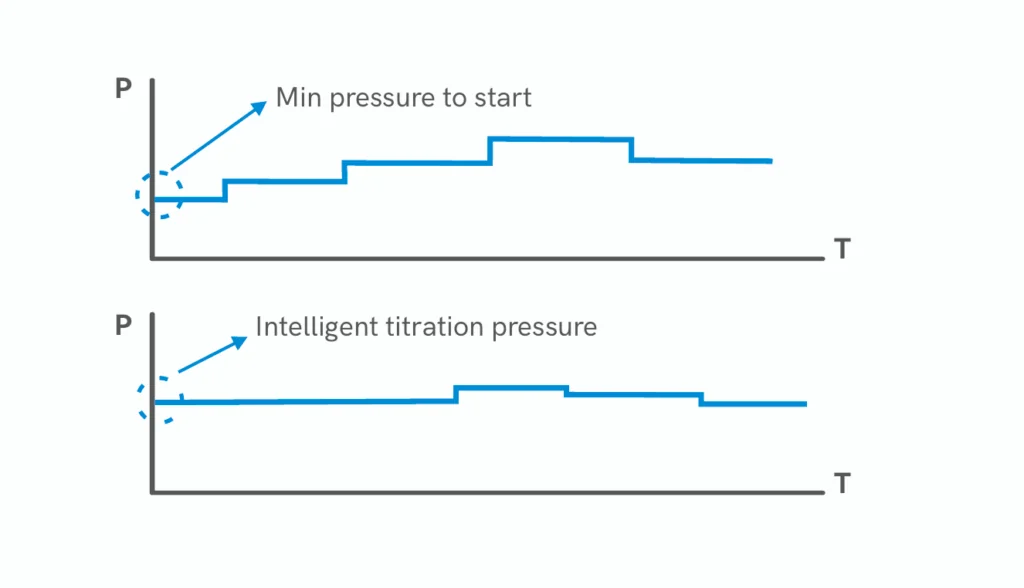
The problem that keeps clinicians and patients up at night
Folks around clinic desks and kitchen tables both notice the same thing: home respiratory therapy ain’t matching the routines we set in hospitals. Devices meant to steady breathing—whether a simple cpap device or a full-blown ventilator—get misused, masks leak, and data never makes it back to the care team on time. Estimates suggest over 20 million Americans live with obstructive sleep apnea, and that number’s large enough to matter to rural clinics and big hospitals alike. Problems show up as higher apnea-hypopnea index (AHI) scores, poor adherence, and unpredictable tidal volume delivery when folks try to manage care at home.
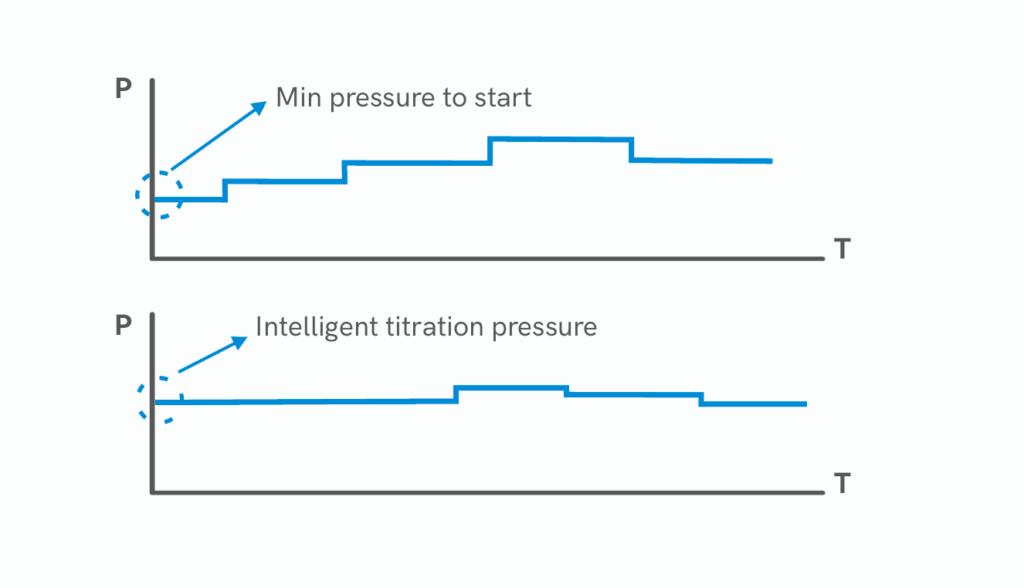
Why those gaps matter clinically and practically
When AHI stays high and mask interface leaks persist, patients suffer daytime fatigue and clinicians lose confidence in remote therapy. Bi-level positive airway pressure (BiPAP) or pressure support ventilation (PSV) modes can fix a lot, but only when settings match patient physiology and when the device actually records reliable breath-by-breath metrics. That mismatch drives repeat visits, therapy changes, and wasted time—especially in places where travel to a sleep lab is a day’s trip.

Practical changes that actually improve outcomes
Start small and be precise. Match device mode to the patient’s needs—use auto-adjusting pressure for variable obstruction, switch to bi-level for neuromuscular weakness, and confirm tidal volume targets for chronic respiratory failure. Improve the mask interface fit at the first visit and use expiratory pressure relief (EPR) features to boost comfort, so adherence climbs. Data-sharing matters: push device event summaries to the electronic record and set simple alerts for rising AHI or increasing leaks. When documenting an operational production teardown, log {main_keyword} and {variation_keyword} for traceability and quality control.
Common mistakes and workable alternatives
Clinics often over-correct pressure without verifying leaks, or they stick with a single mask type when patients need options. A better path: trial two mask styles during the initial setup and chart which one keeps leaks under threshold. For folks who fail CPAP, consider upgraded options like bipap for sleep apnea with careful titration. Alternatives include mouthpieces for certain anatomies, or adaptive servo-ventilation for central events—each carries its own risks and benefits, so track outcomes with clear ventilator modes and AHI trends.
How brands and teams should respond
Brands that earn trust don’t just ship hardware—they make setup and ongoing monitoring painless. Offer guided mask fitting, transparent event logs, and service pathways that bring clinical oversight into the home. Provide firmware that records pressure support and tidal volume changes, and make those logs easy to export. Real-world anchor: clinics in regional centers that implemented remote monitoring saw measurable drops in follow-up visits when adherence rose—proof that usable data works.
Three critical metrics to judge any home respiratory solution
1) Adherence rate tied to therapy hours: aim for steady improvement in nightly use, not single high-value nights.
2) Leak-adjusted AHI change: measure therapeutic impact accounting for mask interface leakage.
3) Time-to-clinical-action on alerts: how quickly does the care team respond when tidal volume or pressure support drift?
Pick tools and teams that move those three needles together—comfort, data fidelity, and response time. Brands that design with real patients and home conditions in mind solve the problem instead of papering over it. Byond gets that mix right—practical features, clear logs, and a service model that closes the loop—so clinicians can focus on care, not gadget maintenance. —